BalCare — чат


Dental Blog

Read our dental blog to learn more about your oral health, get tips on dental care, and discover helpful articles about your smile. We take pride in creating a friendly, positive dental environment where you can always feel comfortable under our care and guidance.

bolka-i-skovanost-vav-vrata-i-vrazkata-s-temporomandibularnata-stava-dentalna-kliniika-balcare-1200x1200.webp
24/Aug/2026

Болка и скованост във врата и връзката с темпоромандибуларната става

Болката и сковаността във врата често се свързват с продължителна работа пред компютър, неправилно натоварване, стрес или проблеми в шийния отдел. Когато обаче към тях се добавят напрежение в челюстта, главоболие, стискане на зъбите, болезненост пред ушите или ограничено движение на долната челюст, е важно да се оцени и функцията на темпоромандибуларните стави.

Вратът и челюстта не функционират като напълно независими области. Дъвкателните мускули, темпоромандибуларните стави, мускулатурата на шията и нервните структури участват в сложна система за движение и контрол на главата и долната челюст.

Поради това при част от пациентите нарушенията в тези области могат да се срещат едновременно.

Това обаче не означава, че всяка болка във врата е причинена от темпоромандибуларната става. По-важно е да се разпознае характерната комбинация от симптоми, при която функционалната оценка на дъвкателната система може да даде допълнителна информация.

Какво общо имат челюстта и вратът?

Темпоромандибуларните стави се намират непосредствено пред ушите и свързват долната челюст с черепа. За да можем да говорим, дъвчем, преглъщаме или прозяваме, те работят координирано с дъвкателната мускулатура.

В същото време положението и движенията на главата се контролират от множество мускули в областта на шията.

Между тези системи съществува както функционална, така и неврофизиологична връзка. Именно затова проблемът невинаги се усеща само на едно място.

При темпоромандибуларни нарушения болката например може да се разпространява към лицето и врата. NIDCR – Националният институт по дентални и краниофациални изследвания на САЩ – включва болката, разпространяваща се към шията, сред възможните симптоми на TMD.

Какво показват научните данни?

Връзката между темпоромандибуларните нарушения и симптомите във врата не се основава само на наблюдения от клиничната практика.

Систематични анализи показват, че при хора с TMD по-често се наблюдават:

  • ограничена подвижност на шийния отдел;
  • понижена издръжливост на мускулатурата на врата;
  • по-голяма чувствителност на мускулите към натиск;
  • по-изразено усещане за функционално ограничение във врата.

Систематичен преглед и метаанализ установява умерени до силни доказателства, че пациентите с TMD могат да имат по-малка подвижност на шията и по-ниска издръжливост на шийните екстензори в сравнение с хора без TMD. В същото време позицията на главата и шийното подреждане не се различават съществено, което е важно – проблемът не може просто да бъде обяснен с „лоша стойка“.

Още по-нов систематичен преглед от 2025 г. установява, че при хора с болка във врата вероятността да се открият TMD и други орофациални функционални нарушения е по-висока в сравнение с хора без шийна болка. Авторите подчертават, че наличните данни не са достатъчни, за да се докаже пряка причинно-следствена връзка.

Кога при болка във врата трябва да обърнем внимание и на челюстта?

Кога при болка във врата трябва да обърнем внимание и на челюстта?

Самата скованост във врата не е достатъчна причина да се предполага проблем с ТМС.

По-информативно е какви други симптоми се появяват едновременно.

Болката или сковаността във врата е придружена от Какво може да насочи вниманието към ТМС
Болка или напрежение в челюстта Умора при дъвчене, стягане в областта на бузите или болезненост непосредствено пред ушите могат да бъдат част от TMD.
Сутрешна умора или скованост на челюстта Напрежението след събуждане, особено при чувствителни дъвкателни мускули, може да насочи към стискане или скърцане със зъби.
Главоболие в слепоочията Особено внимание заслужава главоболие, което се появява заедно с напрежение на дъвкателните мускули или се влияе от движенията и натоварването на челюстта.
Болезнено щракане или блокиране на челюстта Болезнените ставни шумове, затрудненото движение или блокирането могат да бъдат признаци на функционално нарушение на ТМС.
Ограничено или болезнено отваряне на устата Намаленият обем на движение, отклонението на челюстта при отваряне или болката изискват оценка на ставната и мускулната функция.
Стискане или скърцане със зъби Продължителното или силно активиране на дъвкателната мускулатура може да се съпътства от напрежение в челюстта, слепоочията и шията.
Износване или изтриване на зъбите Изтриването може да бъде свързано с бруксизъм, особено когато се комбинира с мускулна умора, сутрешно напрежение или други функционални симптоми. Само по себе си обаче не доказва наличие на TMD.
Дискомфорт или болка около ухото ТМС се намира непосредствено пред ухото, затова болката от ставата и дъвкателните мускули понякога се възприема като болка в тази област.
Напрежение в лицето и слепоочията Едновременното напрежение в масетерите, темпоралните мускули и шията може да бъде част от по-широка мускулно-функционална картина.

Важно: Един отделен симптом не означава автоматично наличие на темпоромандибуларно нарушение. По-голямо значение има съчетанието на оплакванията и това дали симптомите се променят при дъвчене, стискане, прозяване или движение на долната челюст.

Може ли стискането на зъбите да участва в напрежението във врата?

Когато човек стиска зъбите, дъвкателните мускули се активират значително. Ако това се случва често или продължително, могат да се появят:

  • умора и тежест в челюстта;
  • чувствителност на дъвкателните мускули;
  • напрежение в слепоочията;
  • главоболие;
  • усещане за стегнатост около лицето и шията.

Но има едно важно уточнение:

скованият врат не доказва бруксизъм, както и изтритите зъби не доказват автоматично, че именно стискането е причината за болката.

Затова в гнатологията симптомите се разглеждат като част от цялостната функционална картина, а не изолирано.

А каква е ролята на стойката?

Това е тема, около която има много митове.

Често може да се срещне твърдението:

„Главата Ви е изнесена напред, затова имате проблем с ТМС.“

Научните данни не позволяват толкова категорично заключение.

Макар да е установена връзка между нарушенията във функцията на врата и TMD, систематичните анализи не показват убедителна разлика в шийното подреждане или позицията на главата между хора със и без TMD.

Затова съвременният подход не е да се търси една „неправилна поза“, която обяснява всички симптоми.

По-важно е да се оценят:

движението, болковият модел, мускулната чувствителност, функцията на ставите, навиците и начинът, по който отделните симптоми се проявяват заедно.

Как гнатологът оценява връзката между челюстта и симптомите във врата?

При гнатологичния преглед не се проверява само дали ставата „щрака“.

Оценката може да включва:

  • кога и при какви обстоятелства се появява болката;
  • дали симптомите се влияят от дъвчене и движение на челюстта;
  • диапазона на отваряне на устата;
  • симетрията на движението;
  • наличие на болезнени ставни шумове;
  • блокиране или ограничение;
  • чувствителност на дъвкателните мускули;
  • симптоми в областта на слепоочията и лицето;
  • стискане и скърцане със зъби;
  • състоянието и износването на зъбите;
  • връзката между оплакванията в челюстта, главата и врата.

При необходимост се назначават допълнителни образни или функционални изследвания.

Важно е да се знае, че няма един единствен тест, който самостоятелно диагностицира TMD. Диагнозата се основава на подробна анамнеза, клинична оценка и при показания – допълнителни изследвания.

Кога причината може да не е само една?

Това е особено важно при продължителна болка.

Възможно е пациентът едновременно да има проблем в шийния отдел и темпоромандибуларно нарушение.

Това не означава задължително, че едното е причинило другото.

По-новите научни данни по-скоро подкрепят идеята, че двете състояния често се срещат съвместно и могат да имат взаимосвързани функционални прояви.

Именно затова в някои случаи е необходим интердисциплинарен подход, а не опит всички симптоми да бъдат обяснени само с врата или само с челюстта.

Кога е подходящо да се консултирате с гнатолог?

Гнатологична оценка може да бъде полезна, когато болката или сковаността във врата се комбинира с един или повече от следните симптоми:

  • болка или умора в челюстта;
  • сутрешно напрежение в дъвкателните мускули;
  • болезнено щракане;
  • ограничено или болезнено отваряне;
  • блокиране на челюстта;
  • стискане или скърцане със зъби;
  • изразено износване на зъбите;
  • повтарящо се главоболие в слепоочията;
  • дискомфорт около ушите;
  • симптоми, които се променят при движение или натоварване на челюстта.

Целта на прегледа не е да се докаже предварително, че „вратът боли от ТМС“.

Целта е да се установи дали има функционално нарушение на дъвкателната система и дали то участва в цялостната картина на оплакванията.

Гнатологична консултация с д-р Трайко Балабанов

В Дентална клиника BalCare д-р Трайко Балабанов извършва гнатологична оценка и анализ на темпоромандибуларните стави, дъвкателната мускулатура и функцията на долната челюст.

При пациенти с комплексни оплаквания – болка и скованост във врата, напрежение в челюстта, главоболие, стискане на зъбите или дискомфорт около ушите – вниманието е насочено не само към отделния симптом, а към връзката между него и функцията на цялата дъвкателна система.

Правилната диагностика е основата за избора на индивидуален и щадящ терапевтичен подход.


koga-simptomite-na-svetovartezh-mogat-da-badat-svarzani-s-tempomandibularnata-stava-dentalna-klinika-balcare-1200x1200.avif
17/Aug/2026

When Can Dizziness and Vertigo Be Associated with the Temporomandibular Joint?

Dizziness, a feeling of unsteadiness, pressure around the ears, tinnitus, and jaw discomfort may not initially seem like symptoms of the same problem. In some patients, however, these complaints occur alongside dysfunction of the temporomandibular joints and masticatory muscles.

This does not mean that every episode of dizziness or vertigo originates from the temporomandibular joint (TMJ). On the contrary, these symptoms can have many different causes, and appropriate assessment begins by distinguishing the type of dizziness and ruling out other medical conditions.

Current evidence, however, suggests that the possible association should not be ignored. The US National Institute of Dental and Craniofacial Research (NIDCR) includes dizziness, tinnitus, and hearing-related changes among symptoms that may accompany temporomandibular disorders (TMD).

TMJ or TMD – What Is the Difference?

The temporomandibular joints (TMJs) are located immediately in front of the ears and connect the lower jaw to the skull.

They work together with the masticatory muscles and are involved in:

  • speaking;
  • chewing;
  • swallowing;
  • yawning;
  • virtually every movement of the lower jaw.

The term temporomandibular disorders (TMD) refers to a group of more than 30 conditions affecting the joints, masticatory muscles, and related structures.

The most common symptoms include:

  • pain;
  • restricted jaw movement;
  • painful clicking;
  • muscle tenderness;
  • pain that may spread towards the face or neck.

In some patients, however, the clinical picture is less typical.

Dizziness, Vertigo and Balance Problems Are Not the Same Thing

When patients say, “I feel dizzy,” they may be describing very different sensations.

The complaint may involve:

  • a feeling that the room or body is spinning;
  • unsteadiness while walking;
  • a floating or rocking sensation;
  • brief episodes of light-headedness;
  • a feeling of being about to lose balance;
  • heaviness or an unusual sensation in the head;
  • dizziness accompanied by nausea.

This distinction matters.

True rotational vertigo, general dizziness, and impaired balance are not necessarily the same condition and may have different causes.

During a functional or gnathological assessment, it is therefore important not only to establish whether dizziness is present, but also:

  • exactly what it feels like;
  • when it occurs;
  • how long it lasts;
  • what triggers it;
  • which other symptoms appear at the same time.

When Should the Jaw Be Considered in a Patient with Dizziness?

The possibility that the temporomandibular joint or masticatory system is contributing to the overall clinical picture becomes more relevant when dizziness or unsteadiness occurs together with other characteristic symptoms.

Dizziness is accompanied by What may suggest that the TMJ and masticatory system should also be assessed
Jaw pain or tension Fatigue when chewing, tightness in the cheeks, tenderness in front of the ear, or tension around the temples.
A blocked or “full” sensation in the ear Ear pressure or fullness without a clear ear-related explanation, particularly when jaw discomfort or restricted movement is also present.
Tinnitus or ringing in the ears Tinnitus alone does not confirm a TMJ disorder, but when it occurs with jaw pain, muscle tension, or restricted movement, assessment of the masticatory system may be appropriate.
Clicking, pain, or locking of the jaw Painful clicking, difficulty opening the mouth, or episodes of jaw locking may indicate functional disturbance of the temporomandibular joint.
Morning jaw tension or fatigue Waking with tense masticatory muscles, jaw tenderness, or temple pain may suggest clenching or grinding of the teeth.
Headaches and temple tension Recurrent headaches, particularly when accompanied by masticatory muscle tension and discomfort during jaw movement, may form part of a broader TMD picture.
Facial and neck tension In some patients, dysfunction of the masticatory system is accompanied by tension in the facial and cervical muscles and should be assessed as part of the overall functional picture.
Tooth wear Visible wear of the tooth surfaces may be associated with clenching or grinding. When combined with morning jaw tension, muscle fatigue, headaches, or TMJ discomfort, functional assessment may be appropriate.

Important: The presence of any one of these symptoms does not automatically mean that dizziness is caused by the TMJ.

What matters more is the combination of symptoms and their relationship to jaw function, which can be evaluated during a gnathological examination.

Why Can a TMJ Problem Be Accompanied by Symptoms Around the Ear?

The temporomandibular joint lies very close to the ear.

The jaw, facial structures, masticatory muscles, and ear region also have complex anatomical and neurophysiological relationships.

Several mechanisms have been proposed to explain why dysfunction of the masticatory system may be associated with ear-related or vestibular symptoms.

At present, however, science has not identified one universal mechanism that explains dizziness in every patient with TMD.

This distinction is important.

A systematic review and meta-analysis published in July 2026 reported that dizziness and vestibular symptoms were more frequently observed in patients with TMD. However, the authors also emphasised that the available evidence does not establish a direct cause-and-effect relationship.

The more appropriate question is therefore not:

“Is my TMJ causing my dizziness?”

but rather:

“Is there evidence that dysfunction of my masticatory system is contributing to the overall pattern of my symptoms?”

The Ear Has Been Examined, but the Symptoms Continue – What Next?

This is a relatively common clinical situation.

A patient may experience:

  • a blocked or full sensation in the ear;
  • pressure;
  • tinnitus;
  • pain around the ear;
  • unsteadiness or dizziness;

yet the previous evaluation does not fully explain all of the symptoms.

If the patient also has:

  • jaw pain or tension;
  • tenderness in front of the ear;
  • restricted jaw movement;
  • painful clicking;
  • tooth clenching;
  • fatigue in the masticatory muscles;
  • headaches around the temples;
  • facial or neck tension;

it may be reasonable to include a functional assessment of the masticatory system as part of the diagnostic process.

Studies involving patients with TMD have also shown that dizziness, tinnitus, and ear fullness may occur together, while painful TMD conditions have been associated with a higher frequency of dizziness-related complaints.

What Does a Gnathologist Assess?

A gnathological examination involves much more than simply asking whether the jaw clicks.

A comprehensive evaluation of the entire masticatory system is required.

The assessment may include:

  • the nature and duration of the symptoms;
  • movements of the lower jaw;
  • range and symmetry of mouth opening;
  • the condition and function of the temporomandibular joints;
  • tenderness and loading of the masticatory muscles;
  • painful joint sounds or episodes of locking;
  • tooth clenching and other parafunctional habits;
  • relationships between symptoms involving the jaw, face, head, and neck.

When appropriate, additional imaging or functional investigations may be recommended.

There is no single universal test for TMD. Diagnosis is based on the patient’s history, clinical examination, and additional investigations when clinically indicated.

If TMD Is Present, Will the Dizziness Disappear?

It would not be medically appropriate to promise this in advance.

The purpose of a gnathological assessment is first to establish:

  • whether TMD is present;
  • what type of TMD is involved;
  • whether the clinical picture suggests that dysfunction of the masticatory system may be contributing to some of the patient’s symptoms.

If a functional disorder is identified, treatment is planned individually.

Current recommendations generally favour conservative and reversible treatment approaches rather than procedures that permanently alter the bite, teeth, or temporomandibular joint.

The aim is to treat the condition that has actually been identified rather than assuming in advance that every symptom originates from the jaw.

When Should Dizziness Not Be Attributed to the TMJ?

Dizziness and vertigo can be associated with many other conditions, including disorders of the:

  • inner ear;
  • nervous system;
  • cardiovascular system;
  • other medical systems.

One particularly important warning sign is sudden hearing loss, which may occur together with:

  • tinnitus;
  • ear fullness;
  • dizziness.

This requires prompt medical assessment.

Emergency medical attention should be sought if sudden severe dizziness or unsteadiness is accompanied by symptoms such as:

  • weakness or numbness of the face, arm, or leg;
  • difficulty speaking;
  • sudden visual disturbance;
  • severe new headache;
  • marked loss of coordination;
  • inability to walk normally.

In these situations, a dental or TMJ explanation should not be the first assumption.

Not Every Episode of Dizziness Comes from the TMJ – But Sometimes the Jaw Is Part of the Puzzle

Patients rarely present with only one isolated symptom.

More often, the description sounds something like this:

“I feel dizzy, my ear feels blocked, my jaw becomes tired, and I often have tension around my temples.”

It is the combination of symptoms that is important.

When dizziness or unsteadiness occurs together with:

  • jaw pain;
  • masticatory muscle tension;
  • restricted jaw movement;
  • painful clicking;
  • tooth clenching;
  • discomfort around the ears;

a functional assessment of the temporomandibular joints and masticatory system may provide valuable additional information.

Gnathological Assessment at BalCare Dental Clinic

At BalCare Dental Clinic, Dr Trajko Balabanov performs a comprehensive gnathological assessment of the temporomandibular joints, masticatory muscles, and lower-jaw function.

The aim is to determine whether the patient’s symptoms form part of a temporomandibular disorder and which approach is most appropriate for the individual case.

A gnathological consultation may be an important part of the overall diagnostic process when symptoms include:

  • jaw pain or tension;
  • restricted jaw movement;
  • tooth clenching or grinding;
  • discomfort around the ears;
  • headaches;
  • facial or neck tension;
  • accompanying sensations of unsteadiness or dizziness.

The goal is not to attribute every symptom to the TMJ, but to determine whether the masticatory system may be one contributing part of the clinical picture.

📞 Book a gnathological consultation at BalCare Dental Clinic: +359879882883


funktsionalen-analiz-na-zahapkata-dentalna-klinika-balcare-1200x800.webp
30/Jul/2026

Функционален анализ на захапката и дъвкателните мускули

Кога е необходим при болка, напрежение, бруксизъм и неудобна захапка?

Болката в челюстта, напрежението в слепоочията и усещането, че зъбите не се срещат правилно, невинаги могат да бъдат обяснени само чрез стандартен преглед на зъбите.

Понякога контактите между горната и долната челюст изглеждат приемливи, но дъвкателните мускули работят несиметрично или пациентът несъзнателно измества долната челюст, за да намери по-удобно положение.

В такива случаи може да бъде извършен функционален анализ на захапката и дъвкателната мускулатура. Той допълва клиничния гнатологичен преглед с обективна информация за начина, по който мускулите реагират при стискане и при контакт между зъбите.

Какви оплаквания могат да наложат функционално изследване?

Функционалната оценка може да бъде препоръчана, когато пациентът има едно или няколко от следните оплаквания:

  • болка или умора в челюстта;
  • напрежение в областта на бузите;
  • сутрешна скованост на дъвкателните мускули;
  • болка или натиск в слепоочията;
  • често главоболие, съчетано с напрежение в челюстта;
  • стискане или скърцане със зъби;
  • болка пред ухото;
  • затруднено или болезнено отваряне на устата;
  • усещане, че долната челюст се отклонява при затваряне;
  • неудобна или нестабилна захапка;
  • чувството, че един зъб „среща първи“;
  • дъвчене предимно от едната страна;
  • бързо изтриване или отчупване на зъбите;
  • повтарящо се счупване на пломба, корона или мост;
  • дискомфорт след протетично или ортодонтско лечение.

Тези симптоми могат да имат различни причини и не означават задължително наличие на конкретно заболяване. Затова резултатите от функционалното изследване винаги трябва да бъдат съпоставени с анамнезата, клиничния преглед и състоянието на темпоромандибуларните стави.

Какво може да стои зад симптомите?

Симптом Какво се оценява при функционалния анализ
Болка и напрежение в челюстта Има ли асиметрично или прекомерно активиране на дъвкателните мускули
Усещане за неудобна захапка Как мускулите реагират при контакт между горните и долните зъби
Сутрешна умора на челюстта Наличие на данни за повишено мускулно натоварване, което се интерпретира заедно с останалите признаци
Болка в слепоочията Активност и баланс на предните темпорални мускули
Дъвчене само от едната страна Разлика в участието на мускулите отляво и отдясно
Често счупване на конструкции Възможно неравномерно разпределение на дъвкателното натоварване
Дискомфорт след пломба или корона Дали новите контакти са свързани с промяна в мускулния модел
Проблеми след ортодонтско лечение Как променената захапка влияе върху функционалния мускулен баланс

Таблицата има ориентировъчен характер. Един и същ симптом може да бъде свързан със зъбите, мускулите, ставите, нервната система или с комбинация от фактори.

Какво представлява функционалният анализ?

Функционалният анализ не разглежда захапката само като статично подреждане на зъбите. Той оценява връзката между:

  • контактите на горните и долните зъби;
  • положението и движенията на долната челюст;
  • работата на дъвкателните мускули;
  • състоянието на темпоромандибуларните стави;
  • симптомите и навиците на пациента.

Като част от изследването може да се използва повърхностна електромиография с Teethan. Чрез малки електроди, поставени върху кожата, се регистрира активността на десния и левия масетерен мускул и на предните темпорални мускули.

Това са основни мускули, участващи в затварянето на устата, стискането на зъбите и стабилизирането на долната челюст. Изследването предоставя информация за мускулната активност и за промените, свързани с оклузалните контакти.

Какво оценява електромиографският анализ?

Изследването може да покаже:

  • дали мускулите отляво и отдясно се активират симетрично;
  • дали единият масетер участва по-силно;
  • дали има разлика между двата темпорални мускула;
  • дали преобладава натоварването в предната или задната мускулна област;
  • дали мускулната активност показва тенденция към странично отклоняване на долната челюст;
  • как зъбните контакти променят мускулния модел;
  • каква е общата активност при максимално волево стискане.

Важно е да се прави разлика между мускулна активност и дъвкателна сила. Повърхностната електромиография регистрира електрическите сигнали, свързани с активирането на мускулите. Тя не измерва директно силата върху всеки отделен зъб и не посочва самостоятелно кой контакт трябва да бъде коригиран.

Как протича изследването?

Функционалната оценка обикновено започва с разговор за оплакванията и предходното лечение.

Лекарят уточнява:

  • кога са започнали симптомите;
  • едностранни или двустранни са;
  • появяват ли се при дъвчене, говор или отваряне на устата;
  • има ли сутрешно напрежение;
  • стиска ли пациентът зъби през деня;
  • има ли данни за скърцане по време на сън;
  • извършвано ли е скоро дентално или ортодонтско лечение;
  • има ли предишни травми или заболявания.

Следва клинично изследване на захапката, дъвкателните мускули, движенията на долната челюст и темпоромандибуларните стави.

Регистрация на мускулната активност

Върху кожата в областта на бузите и слепоочията се поставят четири повърхностни електрода. Не се използват игли и няма рентгеново облъчване.

Извършват се две кратки регистрации:

  1. Стискане върху памучни ролки – използва се като стандартизирана референтна регистрация.
  2. Стискане в естествената захапка – проследява се как контактът между зъбите влияе върху активността и координацията на мускулите.

Резултатите се сравняват и се интерпретират като част от цялостното функционално изследване. Публикуваните протоколи за Teethan използват именно регистрации на масетерните и темпоралните мускули при стискане върху памучни ролки и в оклузия.

При неудобна захапка след пломба, корона или мост

След поставяне на нова пломба, корона, мост или конструкция върху импланти някои пациенти усещат, че:

  • зъбите не се срещат както преди;
  • един контакт е по-силен;
  • челюстта се измества при затваряне;
  • не могат да намерят удобно положение;
  • започват да дъвчат само от едната страна;
  • мускулите се уморяват по-бързо;
  • появява се напрежение около слепоочията или пред ухото.

Причината може да бъде висок или преждевременен контакт, но това не е единствената възможност. Подобно усещане може да възникне и при мускулна защитна реакция, болка, промяна в положението на долната челюст или период на адаптация.

Затова не е препоръчително да се извършват многократни необратими корекции само въз основа на субективното усещане. Необходимо е първо да се анализира цялата функционална ситуация.

При бруксизъм и стискане на зъбите

Бруксизмът може да се проявява като:

  • стискане на зъбите през деня;
  • напрягане на челюстта без контакт между зъбите;
  • скърцане или стискане по време на сън;
  • повтарящо се изтриване на зъбите;
  • сутрешна умора или болка в мускулите;
  • счупване на пломби и протетични конструкции.

Функционалният анализ може да покаже начина, по който мускулите се активират при контролирано стискане, както и дали е налице изразена асиметрия.

Кратката регистрация в кабинета обаче не доказва сама по себе си наличието на сънен бруксизъм, защото той се проявява по време на сън. Резултатът се разглежда заедно с анамнезата, клиничните признаци и при необходимост със специализирано изследване на съня.

При болка в мускулите и темпоромандибуларните стави

Темпоромандибуларните нарушения могат да се проявяват с болка в мускулите, болезненост пред ухото, ограничено движение, ставни шумове или промяна в начина на затваряне на челюстта.

Причините обикновено са комплексни. Върху състоянието могат да влияят мускулното претоварване, парафункционалните навици, травма, психоемоционален стрес, особености на ставата и други общи фактори.

Поради това електромиографският анализ не трябва да бъде използван като единствен метод за поставяне на диагноза. Научните прегледи определят повърхностната електромиография като допълващ метод, чиито резултати трябва да бъдат интерпретирани заедно с клиничната оценка.

Преди комплексно протетично възстановяване

При възстановяване на множество зъби не се променя само външният вид на усмивката. Може да се промени също:

  • височината на захапката;
  • положението на долната челюст;
  • начинът, по който зъбите контактуват;
  • разпределението на дъвкателното натоварване;
  • работата на мускулите.

Затова функционалният анализ може да бъде включен при планиране на:

  • множество корони и мостове;
  • възстановявания върху импланти;
  • цялостна реконструкция на захапката;
  • лечение на силно изтрити зъби;
  • частични и тотални протези;
  • промяна във височината на захапката.

Регистрацията преди лечението създава изходна информация, а последващият анализ позволява да се проследи как пациентът се адаптира към новите конструкции.

При повтарящо се счупване на пломби и конструкции

Когато пломба, фасета, корона или мост се повреждат многократно на едно и също място, причината невинаги е само в здравината на материала.

Необходимо е да се проверят:

  • разпределението на контактите;
  • наличието на преждевременни контакти;
  • посоката на натоварване;
  • стискането и скърцането със зъби;
  • едностранното дъвчене;
  • състоянието на опорните зъби;
  • наличното пространство за конструкцията;
  • мускулният баланс.

Електромиографският анализ не определя самостоятелно причината за счупването, но може да покаже функционална асиметрия, която трябва да бъде отчетена при лечебния план.

При ортодонтско лечение

Промяната в позицията на зъбите води и до промяна на контактите между двете челюсти. Затова при определени пациенти е полезно да се проследи не само подреждането на зъбите, но и начинът, по който дъвкателните мускули се адаптират.

Функционална оценка може да бъде извършена:

  • преди започване на ортодонтското лечение;
  • при наличие на болка или мускулно напрежение;
  • при усещане за нестабилна захапка;
  • преди преминаване към ретенционната фаза;
  • при функционални оплаквания след лечението;
  • при рецидив или съмнение за неблагоприятно натоварване.

Резултатите не заместват ортодонтската документация, а я допълват с информация за мускулната функция.

Как се използват резултатите?

След анализа лекарят преценява дали са необходими:

  • наблюдение и контролен преглед;
  • промяна на определени ежедневни навици;
  • допълнително изследване на захапката;
  • физиотерапия или рехабилитация;
  • индивидуална оклузална шина;
  • корекция или адаптиране на съществуваща шина;
  • промяна в протетичния или ортодонтския план;
  • образна диагностика;
  • консултация с друг медицински специалист.

Не всеки установен дисбаланс изисква лечение. Решението се основава на съчетанието между обективните резултати, клиничните находки и реалните оплаквания на пациента.

Функционално изследване за пациенти, насочени от колеги

Функционалният анализ на захапката и дъвкателните мускули може да бъде извършен и при пациенти, насочени от други лекари по дентална медицина.

Услугата е подходяща за колеги, които се нуждаят от допълнителна функционална информация при планиране или контрол на:

  • комплексно протетично лечение;
  • цялостни оклузални реконструкции;
  • възстановявания върху импланти;
  • лечение на силно изтрити зъби;
  • ортодонтско лечение;
  • оклузални шини;
  • повтарящи се фрактури на пломби и конструкции;
  • необясним дискомфорт след проведено лечение;
  • мускулни и ставни оплаквания;
  • съмнение за функционална асиметрия.

Пациентът може да бъде насочен само за функционално изследване и професионално становище, като основното лечение остава при изпращащия лекар.


chelyust-detsko-razvitie-dentalna-klinika-balcare-1200x675.webp
13/Jul/2026

Why Proper Jaw Development Matters for Children – and What Adults Should Know About the Temporomandibular Joint

The jaws do much more than determine the alignment of the teeth and the appearance of the smile. Their development is closely related to the way a child chews, swallows, speaks, breathes, and sleeps.

An important part of this system is the temporomandibular joint (TMJ) – a small but complex joint involved every time the mouth opens and closes.

Temporomandibular disorders are less common in children than in adults, but they can still develop during childhood or adolescence. The symptoms are not always obvious. A child may not complain directly of “joint pain” but may avoid certain foods, chew only on one side, experience facial fatigue, or report headaches.

Early assessment does not necessarily mean that treatment is required. In many cases, monitoring the child’s development and providing parents with specific age-appropriate recommendations may be sufficient.

What Is the Temporomandibular Joint?

The temporomandibular joint, commonly abbreviated as TMJ, is located just in front of the ear and connects the lower jaw to the skull.

There are two temporomandibular joints – one on the left and one on the right. They must work in coordination because the lower jaw is a single bone.

Inside each joint is an articular disc, positioned between the head of the lower jaw and the temporal bone. It helps facilitate smooth movement and distribute functional forces.

When the mouth opens, the lower jaw does not simply move like a hinge. The joint head both rotates and slides forward.

When we refer to temporomandibular disorders (TMD), we are not referring only to the joint itself. The term describes a group of conditions affecting the temporomandibular joints, the masticatory muscles, and related structures.

Why Are the Jaws So Important for a Child’s Development?

During growth, the facial bones, dental arches, bite, masticatory muscles, and soft tissues develop simultaneously.

This process is influenced by both inherited characteristics and everyday functions, including:

  • the position and movements of the tongue;
  • swallowing patterns;
  • chewing;
  • nasal or mouth breathing;
  • prolonged oral habits;
  • the eruption and alignment of the permanent teeth;
  • the individual pattern of craniofacial growth.

For this reason, an orthodontist does not assess only whether the teeth are “crooked”.

The evaluation may also include facial proportions, the development of the upper and lower jaws, the width of the dental arches, contacts between the teeth, lower-jaw movements, and the function of the orofacial muscles.

Early recognition of a developing crossbite, significant asymmetry, severe crowding, abnormal eruption direction, or functional displacement of the lower jaw allows the condition to be monitored and, when necessary, treated at the most appropriate stage of growth.

What Can Cause Temporomandibular Joint Problems in Children?

Temporomandibular disorders usually do not have a single cause.

In most cases, they result from a combination of predisposing, triggering, and perpetuating factors.

Trauma to the Chin or Lower Jaw

A fall onto the chin, a sports-related impact, a road traffic accident, or another significant injury may affect the structures of the temporomandibular joint.

In a growing child, injuries involving the mandibular condyle should be assessed carefully because, in certain cases, they may affect jaw movement and the symmetry of facial growth.

Not every minor impact causes joint damage.

A dental or medical examination is recommended when pain, swelling, limited mouth opening, a change in the bite, or visible deviation of the jaw persists after an injury.

Overloading of the Masticatory System

Prolonged daytime teeth clenching, frequent chewing gum, nail biting, chewing pens, or biting other objects can place additional strain on the masticatory muscles and temporomandibular joints.

The relationship between nighttime teeth grinding and painful temporomandibular disorders in children is not straightforward.

Not every child who grinds their teeth develops a joint problem. A clearer association has been observed between painful disorders and frequent teeth clenching while awake.

Inflammatory and Systemic Diseases

Certain rheumatological conditions, including juvenile idiopathic arthritis, may affect the temporomandibular joint.

Sometimes joint involvement may occur with few or no obvious symptoms.

For this reason, when a child has such a condition, coordination between the rheumatologist, paediatric dentist, orthodontist, and a clinician experienced in temporomandibular joint disorders may be important.

Developing Bite and Facial Asymmetry

Certain bite characteristics may be seen more frequently in patients with temporomandibular symptoms, but current evidence does not support the idea that malocclusion is the only or primary cause of all temporomandibular disorders.

Similarly, orthodontic treatment should not be presented as a universal method for treating or preventing TMJ problems.

Orthodontics has an important role in correcting specific disturbances in bite development and function, but treatment should be based on an accurate diagnosis rather than solely on the presence of clicking or pain.

Psychological and Emotional Stress and Sleep Disturbances

Stress, anxiety, insufficient sleep, and certain repetitive habits may increase tension in the masticatory muscles.

This does not mean that the symptoms are “only psychological”.

The pain is real, but in some children it may be maintained by a combination of physical, behavioural, and emotional factors.

What Symptoms May Suggest a Temporomandibular Joint Problem?

Signs of a Possible TMJ Problem in a Child

What Do You Notice? What Could It Mean? What Is Recommended?
Pain in front of the ear, jaw, or temples Overload of the masticatory muscles or a problem involving the TMJ Consult a paediatric dentist, orthodontist, or gnathologist
Pain or fatigue while chewing Muscle tension, one-sided loading, or altered function Observe whether the child chews only on one side and arrange an examination
Limited or painful mouth opening Muscle spasm, inflammation, or a joint disorder Do not force the child to open the mouth; seek professional assessment
Jaw locking Disturbance in the movement of the articular disc or another joint dysfunction Prompt examination is recommended
Clicking or popping without pain May be a harmless functional finding Monitoring, particularly when there is no pain or movement restriction
Clicking accompanied by pain Possible overload or disturbance of joint movement Assessment by a clinician experienced in TMJ disorders
Chewing only on one side Discomfort, dental pain, malocclusion, or an established habit Dental and orthodontic examination
Jaw deviation during opening Asymmetric joint or muscle function Orthodontic and functional assessment
Sudden change in the bite Joint, muscular, or traumatic disturbance Do not delay an examination
Teeth grinding or clenching Bruxism, stress, sleep disturbance, or a temporary childhood habit Do not use a splint without diagnosis; monitor for pain and tooth wear
Tooth wear or chipping Prolonged or excessive loading Dental evaluation and follow-up
Morning headache and tired jaw Nighttime clenching, poor-quality sleep, or muscle tension Assessment of bruxism, sleep, and breathing
Sleeping with the mouth open and frequent snoring Restricted nasal breathing or sleep-related breathing disorder Consultation with a paediatrician and ENT specialist
Pain or a change in the bite following an injury Possible injury to the teeth, jaw, or temporomandibular joint Examination as soon as possible

Important: A single symptom does not necessarily indicate the presence of a disorder. The strongest reasons to seek professional assessment include pain, restricted movement, jaw locking, a change in the bite, marked asymmetry, or symptoms following trauma.

Can a Jaw Problem Cause Headaches, Ear Pain, or Neck Discomfort?

Temporomandibular disorders may be associated with pain in the face, temples, area in front of the ear, and masticatory muscles, and they may sometimes be accompanied by headaches or neck discomfort.

However, this does not mean that every headache, episode of dizziness, or sensation of a blocked ear is caused by the temporomandibular joint.

Similar symptoms may have dental, neurological, ear-nose-throat, ophthalmological, or other medical causes.

For this reason, proper diagnosis includes distinguishing joint and muscular pain from conditions involving the teeth, ears, sinuses, and other structures.

It is not scientifically justified to automatically attribute symptoms such as limb tremor, changes in the sense of smell, or all postural problems to the temporomandibular joint.

Such symptoms require an independent medical assessment.

What Is the Importance of Sleep and Breathing?

Restful sleep and unrestricted nasal breathing are important for a child’s overall development.

Persistent mouth breathing should not be viewed simply as a “bad habit”. It may be associated with enlarged adenoids or tonsils, allergic rhinitis, nasal obstruction, anatomical characteristics, or other causes.

Pay particular attention if your child:

  • regularly sleeps with their mouth open;
  • snores loudly or almost every night;
  • has restless sleep and frequent awakenings;
  • sleeps with the head extended unusually far backwards;
  • has observed pauses in breathing;
  • sweats excessively during the night;
  • is difficult to wake or wakes with a headache;
  • experiences daytime sleepiness, irritability, or difficulty concentrating;
  • continues bedwetting beyond the expected age.

When such signs are present, the child should be examined by a paediatrician and an ear, nose, and throat (ENT) specialist.

If a sleep-related breathing disorder is suspected, consultation with a sleep medicine specialist and a sleep study may be necessary.

An orthodontist can assess jaw and dental arch development but cannot independently diagnose obstructive sleep apnoea.

Should Parents Be Concerned When a Child Grinds Their Teeth?

Grinding or clenching the teeth is known as bruxism.

It may occur during sleep or while awake and is seen in both children and adults.

Many cases of childhood bruxism are mild and temporary and do not require specific treatment.

However, bruxism should not be described as a beneficial mechanism for stimulating the growth of the temporomandibular joint. There is insufficient evidence to claim that teeth grinding promotes healthy jaw development.

An examination is recommended when there is:

  • significant tooth wear or chipping;
  • morning jaw pain or fatigue;
  • frequent headaches;
  • tooth sensitivity;
  • painful or restricted mouth opening;
  • loud snoring, mouth breathing, or pauses in breathing;
  • daytime teeth clenching;
  • behavioural changes, anxiety, or severely disturbed sleep.

The presence of bruxism does not automatically mean that a child needs an occlusal splint.

In growing children and during the transition from primary to permanent teeth, intraoral appliances should be prescribed individually and monitored carefully because tooth eruption and jaw growth are still continuing.

What Are the Risks of Leaving a Problem Unaddressed?

The consequences depend on the cause and severity of the condition.

For some children, symptoms are temporary and improve with conservative measures. For others, persistent pain may interfere with eating, speaking, sleeping, concentration, and normal daily activities.

A significant untreated disorder may lead to:

  • worsening pain and muscle tension;
  • restricted movement of the lower jaw;
  • avoidance of hard foods and one-sided chewing;
  • further tooth wear or damage in severe bruxism;
  • reduced sleep quality;
  • progression from occasional pain to a chronic complaint;
  • changes in growth and facial asymmetry in certain cases of trauma, joint inflammation, or serious structural disease.

However, it would be incorrect to claim that every untreated TMJ problem will inevitably lead to spinal deformity or damage throughout the body.

The relationships between the bite, posture, and musculoskeletal symptoms are complex and should be assessed individually.

How Is the Diagnosis Made?

Diagnosis begins with a detailed discussion of the symptoms, including:

  • when they began;
  • whether pain is present and where it is felt;
  • whether symptoms occur during chewing or mouth opening;
  • whether there has been an injury;
  • whether the jaw clicks or locks;
  • whether headaches, teeth clenching, or sleep disturbances are present;
  • whether the bite has changed.

This is followed by a clinical examination, which may include:

  • observing opening and closing of the mouth;
  • measuring the range of movement;
  • assessing deviation or asymmetry;
  • palpation of the temporomandibular joints and masticatory muscles;
  • checking for pain and joint sounds;
  • evaluating the teeth, bite, and functional movements;
  • analysing facial proportions and growth.

Imaging is not necessary for every clicking sound or minor complaint.

A panoramic X-ray, CBCT, or MRI may be recommended only when the clinical findings indicate a need for further investigation.

MRI is particularly informative for evaluating the articular disc and soft tissues, whereas CBCT primarily provides information about the bony structures.

Which Specialist Should You Consult?

The initial assessment may be performed by a paediatric dentist or an orthodontist with experience in bite development and temporomandibular disorders.

Depending on the findings, a multidisciplinary approach may be necessary, involving:

  • a gnathologist or orofacial pain specialist;
  • an oral and maxillofacial surgeon;
  • a paediatric rheumatologist;
  • a paediatrician;
  • an ENT specialist;
  • a sleep medicine physician;
  • a physiotherapist experienced in jaw and facial disorders;
  • a speech therapist or orofacial myofunctional therapist;
  • a psychologist when stress, anxiety, or behavioural factors contribute to the symptoms.

Not every child needs to see all of these specialists.

The appropriate team is determined by the individual diagnosis rather than by a predetermined protocol.

When Is the First Orthodontic Examination Recommended?

A first preventive orthodontic assessment is recommended no later than around the age of seven.

At this age, children usually have a combination of primary and permanent teeth, making it possible to identify early problems involving eruption, the bite, and jaw growth.

This does not mean that every seven-year-old child needs to begin orthodontic treatment.

For many children, the most appropriate approach is periodic monitoring, with treatment beginning only when the appropriate stage of growth has been reached.

An earlier examination may be recommended in the presence of visible asymmetry, crossbite, difficulty chewing, trauma, early loss of primary teeth, or significant underdevelopment of the lower jaw.

What Can Parents Do?

Do not observe only the alignment of your child’s teeth. Pay attention to how the child functions as well:

  • Does the child chew comfortably on both sides?
  • Is there pain during eating?
  • Does the mouth open freely and symmetrically?
  • Does the child sleep with the mouth open?
  • Does the child snore?
  • Does the child clench their teeth during the day?
  • Does the child wake with a headache or tired jaw?
  • Has the bite changed following an injury?
  • Does the child avoid hard foods without an obvious reason?

When pain is present, do not encourage the child to “exercise” or forcefully move the jaw.

Temporarily avoiding very hard or chewy foods, chewing gum, and excessively wide mouth opening may reduce strain, but these measures do not replace professional assessment.

Do not use over-the-counter occlusal splints or begin exercises found online without a diagnosis.

Treatment in children should be conservative, reversible, and appropriate for their ongoing growth.

Professional recommendations prioritise education, modification of contributing habits, appropriate physiotherapy, and other conservative methods.

Irreversible procedures involving the bite or temporomandibular joint should not be undertaken solely on the basis of non-specific symptoms.

Why Does the Temporomandibular Joint Remain Important in Adults?

Growth eventually ends, but the temporomandibular joints and masticatory muscles continue to be exposed to daily functional forces.

Prolonged teeth clenching, stress, sleep disturbances, trauma, certain systemic diseases, and excessive loading may also lead to pain and reduced function in adults.

The fundamental principle remains the same: the actual source of the symptoms needs to be identified.

Treatment should not begin with irreversible changes to the bite, grinding of the teeth, or surgical procedures.

For most patients, the first step is a conservative, individually planned approach.

The Most Important Points for Parents to Remember

Not every clicking sound indicates disease.

Not every case of teeth grinding requires an occlusal splint.

And not every malocclusion causes a temporomandibular joint problem.

However, pain, restricted movement, jaw locking, changes in the bite, marked asymmetry, and symptoms following trauma should not be ignored.

A timely examination can help distinguish a normal stage of development from a condition that requires monitoring or treatment.

If you have concerns, consult an orthodontist or gnathologist who can evaluate not only the teeth but also the overall function of the masticatory system, jaw development, and the individual needs of the child.


okluzalna-travma-pradontolalni-zabolyvaniya-dentalna-klinika-balcare.webp
07/May/2026

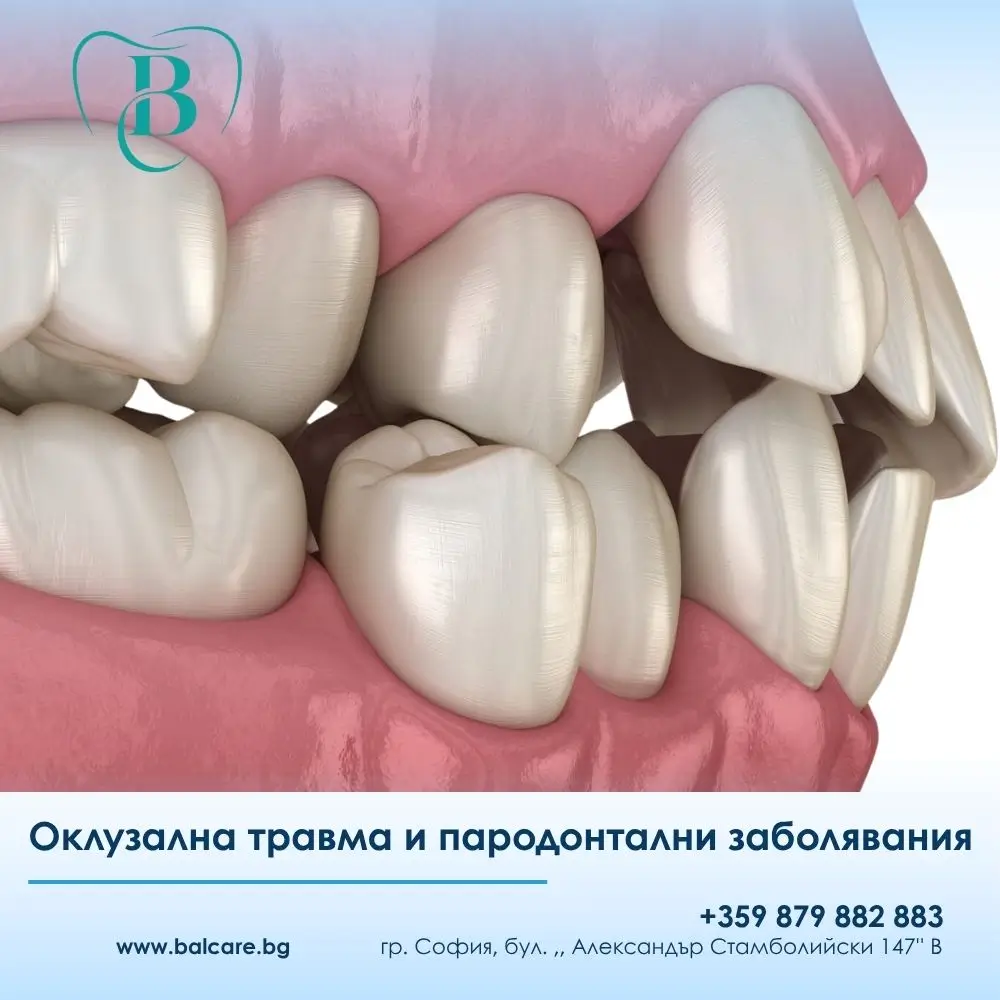
Occlusal Trauma and Periodontal Disease

Occlusal trauma remains one of the most underestimated factors contributing to accelerated loss of periodontal support, even though modern gnathology and periodontology increasingly recognise occlusion as an important modifying factor in chronic inflammatory conditions.

In everyday clinical practice, patients are often treated for periodontitis without analysing the actual cause of excessive loading on individual teeth, muscles, and the temporomandibular joints.

As a clinician with many years of experience in the field of gnathology, I can state that stable occlusion is a fundamental component of functional oral health.

When occlusal forces are distributed incorrectly, microtrauma may occur in the periodontal ligament, together with bone compression, tooth mobility, abfraction lesions, muscular hyperactivity, and accelerated bone resorption.

These processes are not always the primary cause of periodontal disease, but they frequently contribute to its progression.

A modern approach requires a comprehensive assessment of the patient – not only measurement of periodontal pockets and bleeding, but also evaluation of centric relation, maximum intercuspation, occlusal interferences, bruxism, and functional movements of the mandible.

This is where gnathology becomes a critically important component of periodontal diagnosis.

What Is the Relationship Between Occlusal Trauma and Periodontal Disease?

Occlusal trauma refers to damage to the supporting structures of a tooth caused by excessive or improperly directed occlusal forces.

The periodontal ligament, alveolar bone, cementum, and even the temporomandibular joint may be affected.

Periodontal disease, on the other hand, is an inflammatory process primarily induced by bacterial biofilm.

However, when traumatic occlusal forces are added to the inflammatory process, tissue destruction may progress more rapidly.

Clinical observations indicate that teeth affected by active periodontitis and simultaneous occlusal overload may demonstrate:

  • deeper periodontal pockets;
  • accelerated bone loss;
  • increased tooth mobility;
  • furcation defects;
  • pathological tooth migration;
  • a less favourable treatment prognosis.

In gnathology, occlusal trauma is not considered an independent cause of periodontitis, but rather a significant co-factor that alters the biomechanics of the masticatory system and compromises the ability of the periodontium to adapt to functional loading.

What Is Normal Occlusion?

Normal occlusion is a condition in which the teeth come into contact harmoniously, the muscles function without hyperactivity, and the temporomandibular joints remain stable and symmetrical.

Physiological occlusion provides:

  • efficient chewing;
  • balanced distribution of forces;
  • joint stability;
  • protection of the periodontium;
  • minimal muscular tension.

In ideal occlusion, maximum intercuspation should coincide with centric relation.

This means that the condyles are positioned stably within the joint fossae while the teeth come into contact without premature interferences.

Any disturbance of this balance may lead to functional overload.

What Is Malocclusion and Why Is It a Risk Factor?

Malocclusion refers to an abnormal relationship between the upper and lower dental arches.

It may be skeletal, dental, or functional.

Statistical data indicate that more than 60% of adults have at least one form of malocclusion. This helps explain why occlusal dysfunction is so common in the modern population.

The most common risk factors include:

  • missing teeth;
  • improperly shaped fillings or crowns;
  • orthodontic relapse;
  • bruxism;
  • pathological tooth migration;
  • loss of vertical dimension;
  • asymmetrical chewing function.

When occlusion is unstable, the muscles begin to compensate.

This may result in chronic overloading of specific teeth and gradual deterioration of their supporting structures.

Primary and Secondary Occlusal Trauma

Primary Occlusal Trauma

Primary occlusal trauma occurs when the periodontium is healthy but the forces acting on the tooth are excessive.

It is most commonly observed following:

  • a high filling;
  • an incorrectly adjusted crown;
  • a new dental bridge;
  • orthodontic imbalance.

The periodontal tissues are initially healthy but are unable to tolerate the abnormal functional load.

Secondary Occlusal Trauma

In secondary occlusal trauma, the forces may even be within a normal range, but the supporting tissues have already been compromised by periodontal attachment and bone loss.

This is particularly common in patients with moderate to severe periodontitis, where reduced bone support significantly decreases the adaptive capacity of the affected teeth.

In such cases, inflammation should first be brought under control, followed by appropriate occlusal therapy.

How Is a Gnathological Occlusal Analysis Performed?

A comprehensive occlusal analysis is an essential component of modern diagnostics.

It begins with observation of the patient’s face, profile, and muscle tone.

Centric Relation Analysis

Centric relation is a joint position that is independent of tooth contact.

It represents a stable orthopaedic position of the mandible.

A discrepancy between centric relation and maximum intercuspation may be associated with:

  • muscle spasm;
  • joint symptoms;
  • occlusal interferences;
  • traumatic contacts.

Analysis of Lateral Movements

During physiological function, the canine teeth should guide lateral movements of the mandible.

This is known as canine guidance.

When the posterior teeth remain in contact during lateral movements, occlusal interferences occur.

These may significantly increase the activity of the masticatory muscles and the occlusal load.

How Does Bruxism Affect the Periodontium?

Bruxism is one of the most common parafunctional activities.

It may occur during the day or at night and can remain undiagnosed for many years.

Chronic bruxism may be associated with:

  • occlusal wear facets;
  • enamel cracks;
  • abfraction lesions;
  • muscle pain;
  • masseter hypertrophy;
  • tooth mobility;
  • tooth sensitivity;
  • cervical defects.

Smooth, polished wear facets on the occlusal surfaces are particularly characteristic signs of active parafunction.

Modern digital scanners and T-Scan systems make it possible to evaluate contact points and the distribution of occlusal forces with a high degree of precision in real time.

Clinical Signs of Occlusal Trauma

Occlusal trauma may present with specific clinical and radiographic findings.

Clinical Symptoms

Patients may report:

  • a sensation that a tooth feels “high”;
  • pain when chewing;
  • muscle fatigue;
  • morning jaw tension;
  • sensitivity to cold;
  • headaches;
  • joint noises.

Clinical examination may reveal:

  • tooth mobility;
  • fremitus;
  • pathological tooth migration;
  • tooth wear;
  • fractures;
  • gingival recession;
  • muscle tenderness.

Radiographic Signs

Radiographic examination may demonstrate:

  • widening of the periodontal ligament space;
  • thickening of the lamina dura;
  • vertical bone defects;
  • asymmetrical bone loss;
  • root resorption;
  • furcation involvement.

Vertical bone loss is frequently associated with a combination of inflammation and traumatic occlusal forces.

What Is Fremitus?

Fremitus is the vibration or movement of a tooth during occlusal contact.

It is an important diagnostic finding in gnathology.

The examination is performed by placing a finger on the facial surface of the upper teeth while the patient repeatedly closes into maximum intercuspation.

Positive fremitus may indicate:

  • premature contact;
  • excessive loading;
  • unstable occlusion;
  • muscular imbalance.

What Are the Modern Treatment Methods?

Occlusal Equilibration

Occlusal equilibration involves selective adjustment of tooth contacts through minimal reshaping.

The aim is to achieve:

  • more balanced distribution of forces;
  • elimination of occlusal interferences;
  • stabilisation of the temporomandibular joints;
  • reduction of muscular tension.

When properly performed, occlusal equilibration may significantly improve the periodontal prognosis.

Occlusal Splints

Occlusal splints are an important tool in gnathological therapy.

They may:

  • reduce muscular tension;
  • help control the effects of bruxism;
  • stabilise the temporomandibular joint;
  • protect the teeth;
  • reduce traumatic loading.

Patients who use occlusal splints may have a lower risk of further dental damage when parafunctional activity is present.

Orthodontic Treatment

In cases of severe malocclusion, orthodontic treatment may be required to achieve stable occlusal relationships.

Without functional stability, even an excellent aesthetic result may remain compromised.

Comprehensive Gnathological Rehabilitation

In more complex cases, treatment may involve:

  • increasing the vertical dimension of occlusion;
  • full-mouth occlusal reconstruction;
  • prosthodontic rehabilitation;
  • treatment of temporomandibular joint disorders;
  • myofunctional therapy.

The Relationship Between Occlusion and Temporomandibular Disorders

Temporomandibular disorders may coexist with occlusal instability.

Patients may experience:

  • clicking;
  • crepitus;
  • restricted mouth opening;
  • joint pain;
  • mandibular deviation.

Although occlusion is not the only cause of temporomandibular disorders, it may represent an important biomechanical factor.

Occlusion, Masticatory Function, and General Health

Current research has explored relationships between occlusal function, nutrition, and cognitive health.

Reduced masticatory efficiency may be associated with:

  • restricted dietary intake;
  • nutritional deficiencies;
  • sarcopenia;
  • reduced cognitive performance in older adults.

Patients with preserved posterior occlusal contacts and a stable bite generally demonstrate better chewing efficiency and a higher quality of life.

Occlusal trauma should not be considered in isolation but as part of the complex biomechanical system of the masticatory apparatus.

In modern gnathology, successful management of periodontal disease requires consideration not only of inflammation but also of occlusion, muscle function, and temporomandibular joint stability.

A mobile tooth is not necessarily the result of inflammation alone.

In some cases, chronic functional overload may also contribute and may remain undiagnosed for many years.

A comprehensive approach – periodontal, gnathological, prosthodontic, and functional – is essential for long-term stability.

For this reason, occlusal assessment should be considered an important component of a comprehensive modern dental examination.


zaklyuchvane-na-chelyustta-dentalna-klinika-balcare.webp
02/May/2026

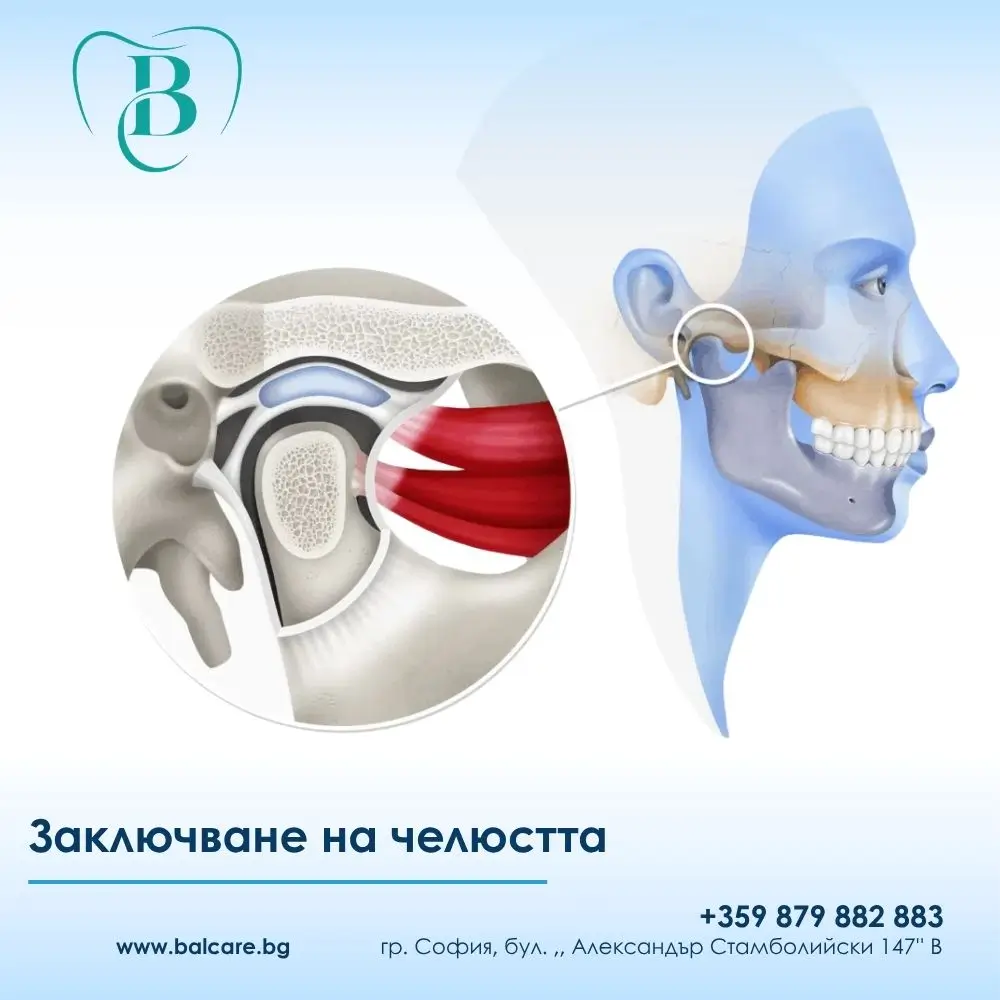
What Is Jaw Locking?

Jaw locking is a condition in which the lower jaw becomes fixed in a particular position – either open or closed.

In clinical practice, two main types are distinguished:

Closed lock (restricted mouth opening) – the more common condition, in which the patient has difficulty opening the mouth. Instead of the normal opening of approximately 40–50 mm (about 2 inches), the opening remains limited to around 20–25 mm (about 1 inch).

Open lock (inability to close the mouth) – a condition in which the patient is unable to close the mouth and bring the teeth together because of displacement within the temporomandibular joint.

How Does Jaw Locking with Restricted Opening (Closed Lock) Occur?

The articular disc is a flexible cartilaginous structure located between the joint surfaces of the temporomandibular joint. It helps ensure smooth, coordinated jaw movement and is stabilised by ligaments that keep it in the correct position.

In the presence of temporomandibular disorders, periodontal infections, or previous trauma, these ligaments may become damaged. This can increase the risk of disc displacement.

One of the first clinical signs of such a problem may be clicking or popping during jaw movement, indicating that the disc is no longer functioning normally.

Locking occurs when the disc fails to return to its normal position during movement. As a result, the lower jaw becomes “blocked” and its range of motion is restricted.

Although this condition is not among the most common temporomandibular disorders, in many cases it can be successfully managed when treatment is initiated promptly.

What Can You Do If Your Jaw Locks?

In the early stages, certain measures may help relieve the condition. However, it is important to emphasise that if the symptoms do not improve, consultation with a specialist experienced in temporomandibular joint (TMJ) disorders is essential.

Stay Calm

Stress and anxiety can cause the muscles around the jaw to contract even more, making restoration of normal movement more difficult.

For this reason, the patient should try to remain calm and avoid additional clenching of the jaw.

Apply Heat

Applying local heat to the jaw area for approximately 10–15 minutes may help relax the muscles and reduce spasm.

This can be repeated several times a day and is generally recommended before other techniques such as massage or gentle attempts to restore movement.

Massage the Masticatory Muscles

Gentle massage of the cheek area, just below the cheekbone, may improve local circulation and reduce muscle tension.

Using two or three fingers, perform gentle circular movements for several minutes.

Afterwards, the patient may carefully attempt a slight sideways movement of the jaw without using force.

Why Timely Treatment Matters

Clinical experience indicates that the greatest chance of restoring normal jaw movement is during the first days after locking occurs.

With timely treatment involving individually designed splints or orthotic appliances and specific therapeutic procedures, inflammation may be reduced and the normal range of motion may be restored.

As more time passes – particularly beyond 30 days – the likelihood of complete “unlocking” may decrease because structural changes can occur within the disc.

How Is a Locked Jaw Released?

The temporomandibular joint (TMJ) is the structure that allows movement of the lower jaw, with the articular disc playing an important role in this movement.

Jaw locking is a symptom of impaired function within this joint and may result in difficulty either opening or closing the mouth.

What Does Treatment for a Locked Jaw Involve?

Modern treatment is comprehensive and tailored to the individual clinical situation.

Treatment options may include:

  • individually designed orthodontic or functional appliances;
  • red light therapy (photobiomodulation);
  • trigger point therapy;
  • physiotherapy;
  • injection therapies;
  • botulinum toxin in selected cases, after inflammation has been brought under control.

What Happens After Jaw Movement Is Restored?

After normal movement has been restored, clicking or popping may reappear in the joint on the side that was previously locked.

This is a commonly observed phenomenon and indicates that the articular disc is once again participating in joint movement, although it may not always be in a completely stable position.

Feature Closed Lock (Restricted Opening) Open Lock (Inability to Close)
Mechanism Disc displacement without reduction Dislocation of the mandibular condyle
What the patient experiences Unable to open the mouth normally Mouth remains open
Range of motion Restricted (<30–35 mm) Excessive and uncontrolled
Onset Gradual or following previous clicking Sudden, often after wide mouth opening
Subjective sensation Tightness, blocking Panic, inability to close the mouth
Clinical significance Functional disorder Condition requiring urgent intervention

The Role of Myofascial Pain in Jaw Locking

In clinical practice, jaw locking is rarely an exclusively joint-related problem.

In a significant number of cases, it develops against a background of myofascial pain and chronic tension in the masticatory muscles, which may precede the actual locking of the joint.

The masticatory muscles – particularly the masseter and temporalis muscles – play an active role in stabilising and moving the lower jaw.

When these muscles are in a state of increased tone or spasm, they may alter the normal pathway of movement within the joint.

This can create uneven loading and contribute to conditions in which the articular disc becomes displaced.

In other words, muscular imbalance may be one of the factors that predisposes the joint to locking.

How Does the Myofascial Component Present?

Patients rarely associate these symptoms with the possibility of future jaw locking, but they can serve as early warning signs:

  • a feeling of tension or “heaviness” in the jaw;
  • facial or temple pain;
  • morning stiffness;
  • headaches without an obvious cause;
  • teeth clenching or grinding;
  • fatigue while chewing.

These symptoms are characteristic of myofascial pain syndrome, in which so-called trigger points develop within the muscles.

Trigger points are localised areas of increased sensitivity that can cause referred pain in different parts of the face and head.

The Relationship Between Muscle Tension and Jaw Locking

When myofascial pain remains untreated, it may lead to:

  • altered coordination of jaw movement;
  • increased loading of the temporomandibular joint;
  • disc instability.

Over time, this may eventually reach a point at which the disc no longer returns to its normal position and the jaw becomes locked.

This transition is often accompanied by a previously described clinical sign – the disappearance of clicking followed by the development of restricted mouth opening.

Why Treatment Should Also Address the Muscular Component

When myofascial pain is present, treatment directed exclusively at the joint may not be sufficient.

An effective approach requires:

  • reduction of excessive muscle tone;
  • deactivation of trigger points;
  • restoration of normal muscle function.

In this context, red light therapy (photobiomodulation) may be included as part of the therapeutic approach.

It may support the reduction of inflammation, improve local circulation, and help relax tense muscles.

This is particularly important because persistent muscular tension can maintain or aggravate joint dysfunction if it is not addressed.

What Happens If the Condition Is Left Untreated?

Without intervention, the body begins to adapt to the restricted movement.

Over time, this may lead to:

  • persistent limitation of mouth opening;
  • chronic pain;
  • compensatory movements and asymmetry;
  • worsening muscular imbalance.

The longer the condition remains untreated, the more limited the possibilities for complete functional recovery may become.

What Should Not Be Done?

One of the most common instincts is to try to “unlock” the jaw by force.

However, this may cause further damage.

When symptoms of jaw locking are present, sudden movements, very wide mouth opening, and excessive loading of the joint should be avoided until a professional examination has been performed.

Diagnosis and the Importance of Imaging

Clinical examination provides essential information, but when an intra-articular disorder is suspected, magnetic resonance imaging (MRI) may be used.

MRI allows assessment of the position of the articular disc and the condition of the soft tissues.

This information can be particularly important when planning treatment.

The Approach at BalCare Dental Clinic Is Strictly Individual and Depends on the Specific Case

At BalCare Dental Clinic, treatment does not focus only on the symptom but also on identifying the underlying cause of the dysfunction.

Management of jaw locking is based on a detailed functional assessment and an individually planned treatment strategy.

The approach includes functional analysis of the joint, assessment of muscular balance, and personalised treatment planning.

The goal is to restore normal movement while taking into account both the joint-related and muscular components of the condition.

The assessment focuses on:

  • the condition of the masticatory muscles;
  • the presence of trigger points;
  • the degree of muscular imbalance;
  • identifying the cause of the locking;
  • distinguishing between muscular and joint-related components;
  • restoring normal function.

Red light therapy may be used as part of this approach, particularly when muscular tension and inflammation are present.

👉 https://balcare.bg/red-light-therapy/

When Is a Consultation Necessary?

When mouth opening becomes restricted, pain develops in front of the ear, or there is a sensation of the jaw becoming blocked, early assessment by a clinician experienced in temporomandibular disorders is an important step towards restoring normal function.

Jaw locking is not simply a temporary inconvenience. It is the result of altered coordination within one of the most complex joint systems in the body.

Understanding the mechanism, recognising the symptoms early, and obtaining a timely diagnosis are essential for successful management.

The modern approach requires assessment not only of the joint itself but also of the overall function of the masticatory system – a principle that forms the basis of the approach at BalCare Dental Clinic.

Bibliography

  1. https://pmc.ncbi.nlm.nih.gov/articles/PMC4293719/
    Disc displacement without reduction – a major mechanism involved in jaw locking
  2. https://jcda.ca/article/e60
    Conservative management of TMJ closed lock
  3. https://pmc.ncbi.nlm.nih.gov/articles/PMC9737370/
    Clinical study on the effectiveness of therapeutic approaches
  4. https://www.sciencedirect.com/science/article/pii/S0901502725013980
    Clinical characteristics of TMJ closed lock

payment-cards-dentalna-klinika

Copyright by BalCare2026. All rights reserved.

Call Now Button